Quick answer
Knee cartilage repair options depend more on the defect and the whole knee than on the treatment name. Small, contained defects may suit activity changes, physiotherapy, injections, or microfracture, while larger or deeper defects may need graft or cell-based surgery. Alignment, meniscus damage, arthritis, age, goals, and rehabilitation time often decide the safest choice.
Key takeaways
- A focal cartilage defect is a local surface injury, not always the same as whole-knee osteoarthritis.
- No current cartilage repair method reliably recreates normal hyaline cartilage in every patient.
- The right choice depends on defect size, depth, location, knee alignment, meniscus health, symptoms, and rehabilitation demands.
What is actually damaged in a focal knee cartilage defect?
A focal knee cartilage defect is a local injury in the smooth articular cartilage that covers the end of the femur, tibia, or kneecap, rather than the same thing as whole-knee osteoarthritis. Articular cartilage is living tissue, but the living cells inside it, called chondrocytes, are sparse and have a poor blood supply. Chondrocytes maintain a firm mesh of type II collagen and water-holding molecules called proteoglycans, which let the joint surface glide and spread load.
When a defect forms, chondrocytes around the damaged area may die or reduce repair work, and the collagen-proteoglycan mesh can split or lose its water balance. If the injury reaches the subchondral bone, the hard bone plate under the cartilage becomes exposed to forces it was not built to take directly. The result can be sharp pain when standing from a chair, swelling after walking downhill, catching on stairs, or aching after sport.
The hardest part to understand is that cartilage repair is not like replacing a tile with the same tile. A full-thickness cartilage defect is more like a pothole in a smooth road that reaches the hard base layer; filling the hole can improve the surface, but the patch material and the original road do not always have the same structure. Focal chondral defects can cause pain and loss of function, especially in younger people who ask more from the knee.3
Why do doctors not offer the same knee cartilage repair option to everyone?
Doctors do not offer the same knee cartilage repair option to everyone because a cartilage defect succeeds or fails inside a whole knee, not in isolation. The key details are the defect size in square centimeters, depth, location, whether the edge is contained, and whether bone under the cartilage is involved. A small defect on the femoral condyle may behave very differently from a larger defect behind the kneecap, where bending the knee during stairs can create high contact pressure.
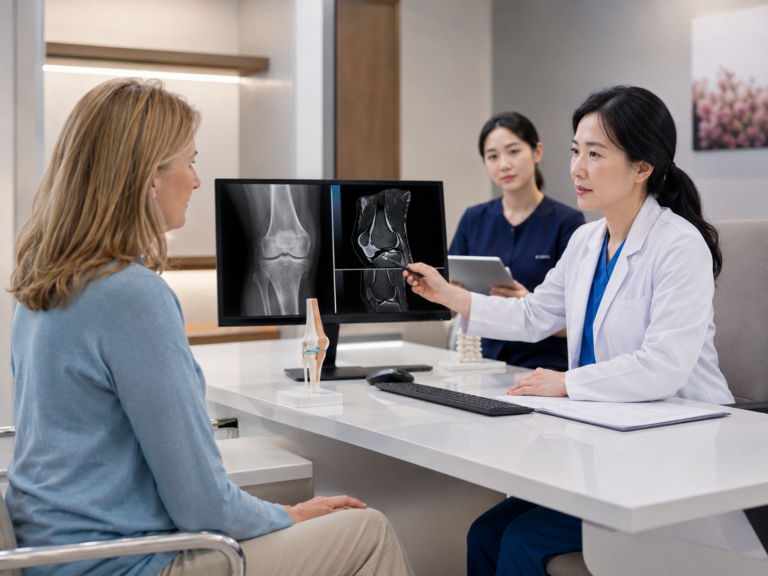
Your surgeon will usually compare the MRI scan with weight-bearing X-rays, sometimes including a long-leg alignment film from hip to ankle. The MRI shows cartilage, bone marrow swelling, meniscus tears, and ligament injury. The standing X-rays show whether the leg loads the inner or outer side of the knee more heavily, which matters because a repair placed under constant overload may break down.
The meniscus also changes the decision because the meniscus spreads load, absorbs shock, and helps stabilize the knee.1 A root tear of the meniscus can make the meniscus stop working like a load-sharing ring, so cartilage overload may progress if the root problem is ignored.1 For the same reason, untreated ligament looseness, severe bow-leg or knock-knee alignment, or widespread arthritis may make an isolated cartilage repair a poor match.
What can conservative care and injections realistically do?
Conservative care can reduce pain, swelling, and overload around a focal cartilage defect, but conservative care cannot reliably rebuild a full-thickness cartilage crater into normal joint surface. Non-surgical treatment is often tried first when symptoms are manageable, arthritis is early, and no loose fragment is blocking motion.5 A plan may include reducing impact running, building quadriceps and hip strength, changing stair or squat habits for a period, using anti-inflammatory medicine when safe, and treating swelling early.
Exercise helps because stronger thigh and hip muscles reduce the sudden peak forces that hit the damaged patch when you stand up after sitting or step down from a curb. Exercise has evidence as an effective conservative approach for knee degeneration.5 The goal is not to “grow cartilage” by exercise alone; the goal is to make the joint quieter and help you learn whether symptoms are controlled enough to avoid or delay surgery.
Injections may be discussed when pain and swelling limit rehabilitation. Corticosteroid injections can calm inflamed synovium, the joint lining, but repeated use has to be considered carefully. Hyaluronic acid, platelet-rich plasma, and bone marrow aspirate concentrate injections are used in some settings, but the evidence, preparation methods, and regulations differ by country. Reviews of non-surgical treatment report limited evidence on combinations of treatments, which is close to real life because many patients use exercise, medicine, and injections together.5
How do the main surgical options differ?
Surgical knee cartilage repair options differ by whether they smooth symptoms, stimulate scar-like repair tissue, transfer bone-cartilage plugs, or implant cells to form repair tissue. Arthroscopic chondroplasty, also called debridement, trims unstable cartilage flaps during arthroscopy (keyhole surgery through small cuts). Chondroplasty may help catching from loose edges, but chondroplasty does not fill a deep defect with new cartilage.
Microfracture makes tiny holes in the subchondral bone so marrow blood and repair cells form a clot over the defect. That clot can mature into fibrocartilage, a repair tissue with more type I collagen than normal hyaline cartilage. Reviews describe simple arthroscopic debridement or microfracture as common first-line surgical choices for smaller lesions,3 and another review states that smaller lesions under 2 cm² are often treated with microfracture or osteochondral autograft transfer.4
Osteochondral autograft transfer moves small plugs of your own bone and cartilage from a lower-load area to the defect. Osteochondral allograft uses donor bone and cartilage, often for larger or deeper defects with bone involvement. Autologous chondrocyte implantation, or ACI, takes your cartilage cells, grows them, and implants them later under a membrane or scaffold; matrix-assisted forms use a carrier sheet. Intermediate defects have shown similar results with osteochondral autograft transfer or ACI in reviews, while larger defects over 4 cm² are often considered for ACI or osteochondral allograft.4
Cell-based and scaffold-based options, including products available only in certain countries, need careful discussion of licensing, evidence, cost, and follow-up. In Korea, some patients ask about CARTISTEM, an allogeneic umbilical cord blood-derived cell product combined with a scaffold; availability in Korea does not mean approval or the same indication in another country. No surgical technique can reliably reproduce normal hyaline cartilage in every patient.4
How should I compare options before deciding?
You should compare knee cartilage repair options by asking what physical problem each option is trying to solve and what you must do after treatment for the repair to have a fair chance. A treatment aimed at calming synovial inflammation is different from a treatment aimed at filling a cartilage-bone defect. A treatment that works best for a small contained lesion may be a poor fit for a large uncontained lesion, and a repair may fail sooner if the meniscus, ligament stability, or leg alignment is not addressed.
The evidence also has limits that should shape your expectations. Surgical options such as osteotomy, osteochondral grafting, marrow stimulation, and autologous chondrocyte implantation are used earlier in disease to address joint structure, but evidence that these operations reduce the long-term risk of osteoarthritis is less certain than evidence for pain and function outcomes.2 If the knee already has severe end-stage osteoarthritis, total knee replacement is the established surgical option rather than focal cartilage repair.2
Before choosing, ask your doctor these questions:
- What is the exact size, depth, and location of my defect on MRI?
- Is the subchondral bone involved, and is there bone marrow swelling?
- Do my standing X-rays show early osteoarthritis or poor alignment?
- Is my meniscus root, meniscus rim, or anterior cruciate ligament contributing to overload?
- What tissue is expected to fill the defect, and how strong is that tissue over time?
- How long will I use crutches, avoid stairs, or delay running?
Seek prompt medical care if the knee locks and will not straighten, swelling comes with fever or redness, calf pain or shortness of breath occurs, or you cannot bear weight after a new injury. For a planned decision, one concrete step today is to gather your MRI images, MRI report, and weight-bearing X-rays, then ask for a visit focused on matching the repair plan to the whole joint. The controlling question is not “Which cartilage repair is newest?” but “Which option fits the defect, the loading forces, and the recovery I can actually complete?”
Frequently asked questions
Can a cartilage injection repair the hole in my knee cartilage?
An injection usually cannot be counted on to fill a full-thickness cartilage hole with normal cartilage. Some injections can reduce pain or swelling, and some biologic injections are being studied, but preparation methods and regulations differ by country. Ask whether the goal is symptom control, tissue repair, or delaying surgery.
Is microfracture enough for my cartilage defect?
Microfracture may be enough for some small, contained defects, especially when alignment, meniscus function, and ligament stability are good. Microfracture relies on marrow clot formation and fibrocartilage repair tissue, so larger defects, high-impact goals, or bone involvement may lead your surgeon to discuss graft or cell-based options.
When is knee replacement considered instead of cartilage repair?
Knee replacement is usually considered when arthritis is widespread and symptoms come from the whole joint, not one contained cartilage defect. Focal cartilage repair is mainly designed for a limited damaged area. If standing X-rays show severe joint-space loss across a compartment, isolated cartilage repair may not address the main pain source.
What should I bring to a cartilage repair consultation?
Bring the MRI images, not only the written report, plus weight-bearing knee X-rays and any long-leg alignment film if you have one. Also write down what hurts most: stairs, squatting, running, standing after sitting, or first steps in the morning. Those details help match the option to the forces on your knee.
References
- Surgical treatment of complex meniscus tear and disease: state of the art. Journal of ISAKOS : joint disorders & orthopaedic sports medicine. 2021 Jan. PubMed 33833044
- Surgical therapy in osteoarthritis. Osteoarthritis and cartilage. 2022 Aug. PubMed 35183776
- The Large Focal Isolated Chondral Lesion. The journal of knee surgery. 2023 Mar. PubMed 34507359
- Knee Articular Cartilage Repair and Restoration Techniques: A Review of the Literature. Sports health. 2016 Mar-Apr. PubMed 26502188
- Non-surgical treatments for the management of early osteoarthritis. Knee surgery, sports traumatology, arthroscopy : official journal of the ESSKA. 2016 Jun. PubMed 27043347
- Cell Transplantation Techniques for Cartilage Restoration. Sports medicine and arthroscopy review. 2025 Dec 1. PubMed 41177986